bone metastases are much commoner than primary bone cancer.
Symptoms, risk, screening and diagnostic confirmation
Detect Bone Cancer and Bone Metastases is about choosing the right test for the right risk.
A bone cancer detection guide separating rare primary bone cancers from common bone metastases, covering pain, x-ray, MRI, bone scan, PET-CT and biopsy.
can reveal destructive or sclerotic lesions.
best for marrow and soft-tissue extension.
must be planned carefully for primary tumors.
Brief outline
What bone cancer and bone metastases means.
Most cancer found in bone is secondary spread from breast, prostate, lung, kidney, thyroid or myeloma. Primary bone cancers such as osteosarcoma, chondrosarcoma and Ewing sarcoma are rare.
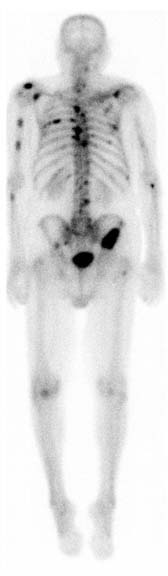
Detection frame
Screening is for people without symptoms. Diagnosis is for symptoms, abnormal examination, family history, imaging findings or abnormal labs. The same test can be sensible in one setting and misleading in another.
Do not ignore
Symptoms and signs not to ignore.
Risk and genetics
Demographics, risks and genetics.
Screening
Who should actually be screened?
There is no population screening for primary bone cancer. People with known cancers may have staging or symptom-led bone imaging.
X-ray
Often the first test for focal bone pain or swelling.
MRI
Maps marrow, soft tissue and surgical planes.
Bone scan/PET-CT/CT
Used for metastatic disease depending on cancer type.
Calcium, ALP, CBC, SPEP
Can point toward metastases or myeloma.
Image-guided biopsy
Planned with the treating team so the biopsy track can be removed if needed.
Spine MRI
Urgent for suspected cord compression.
Images, labs and tissue
Useful tests and what they can miss.
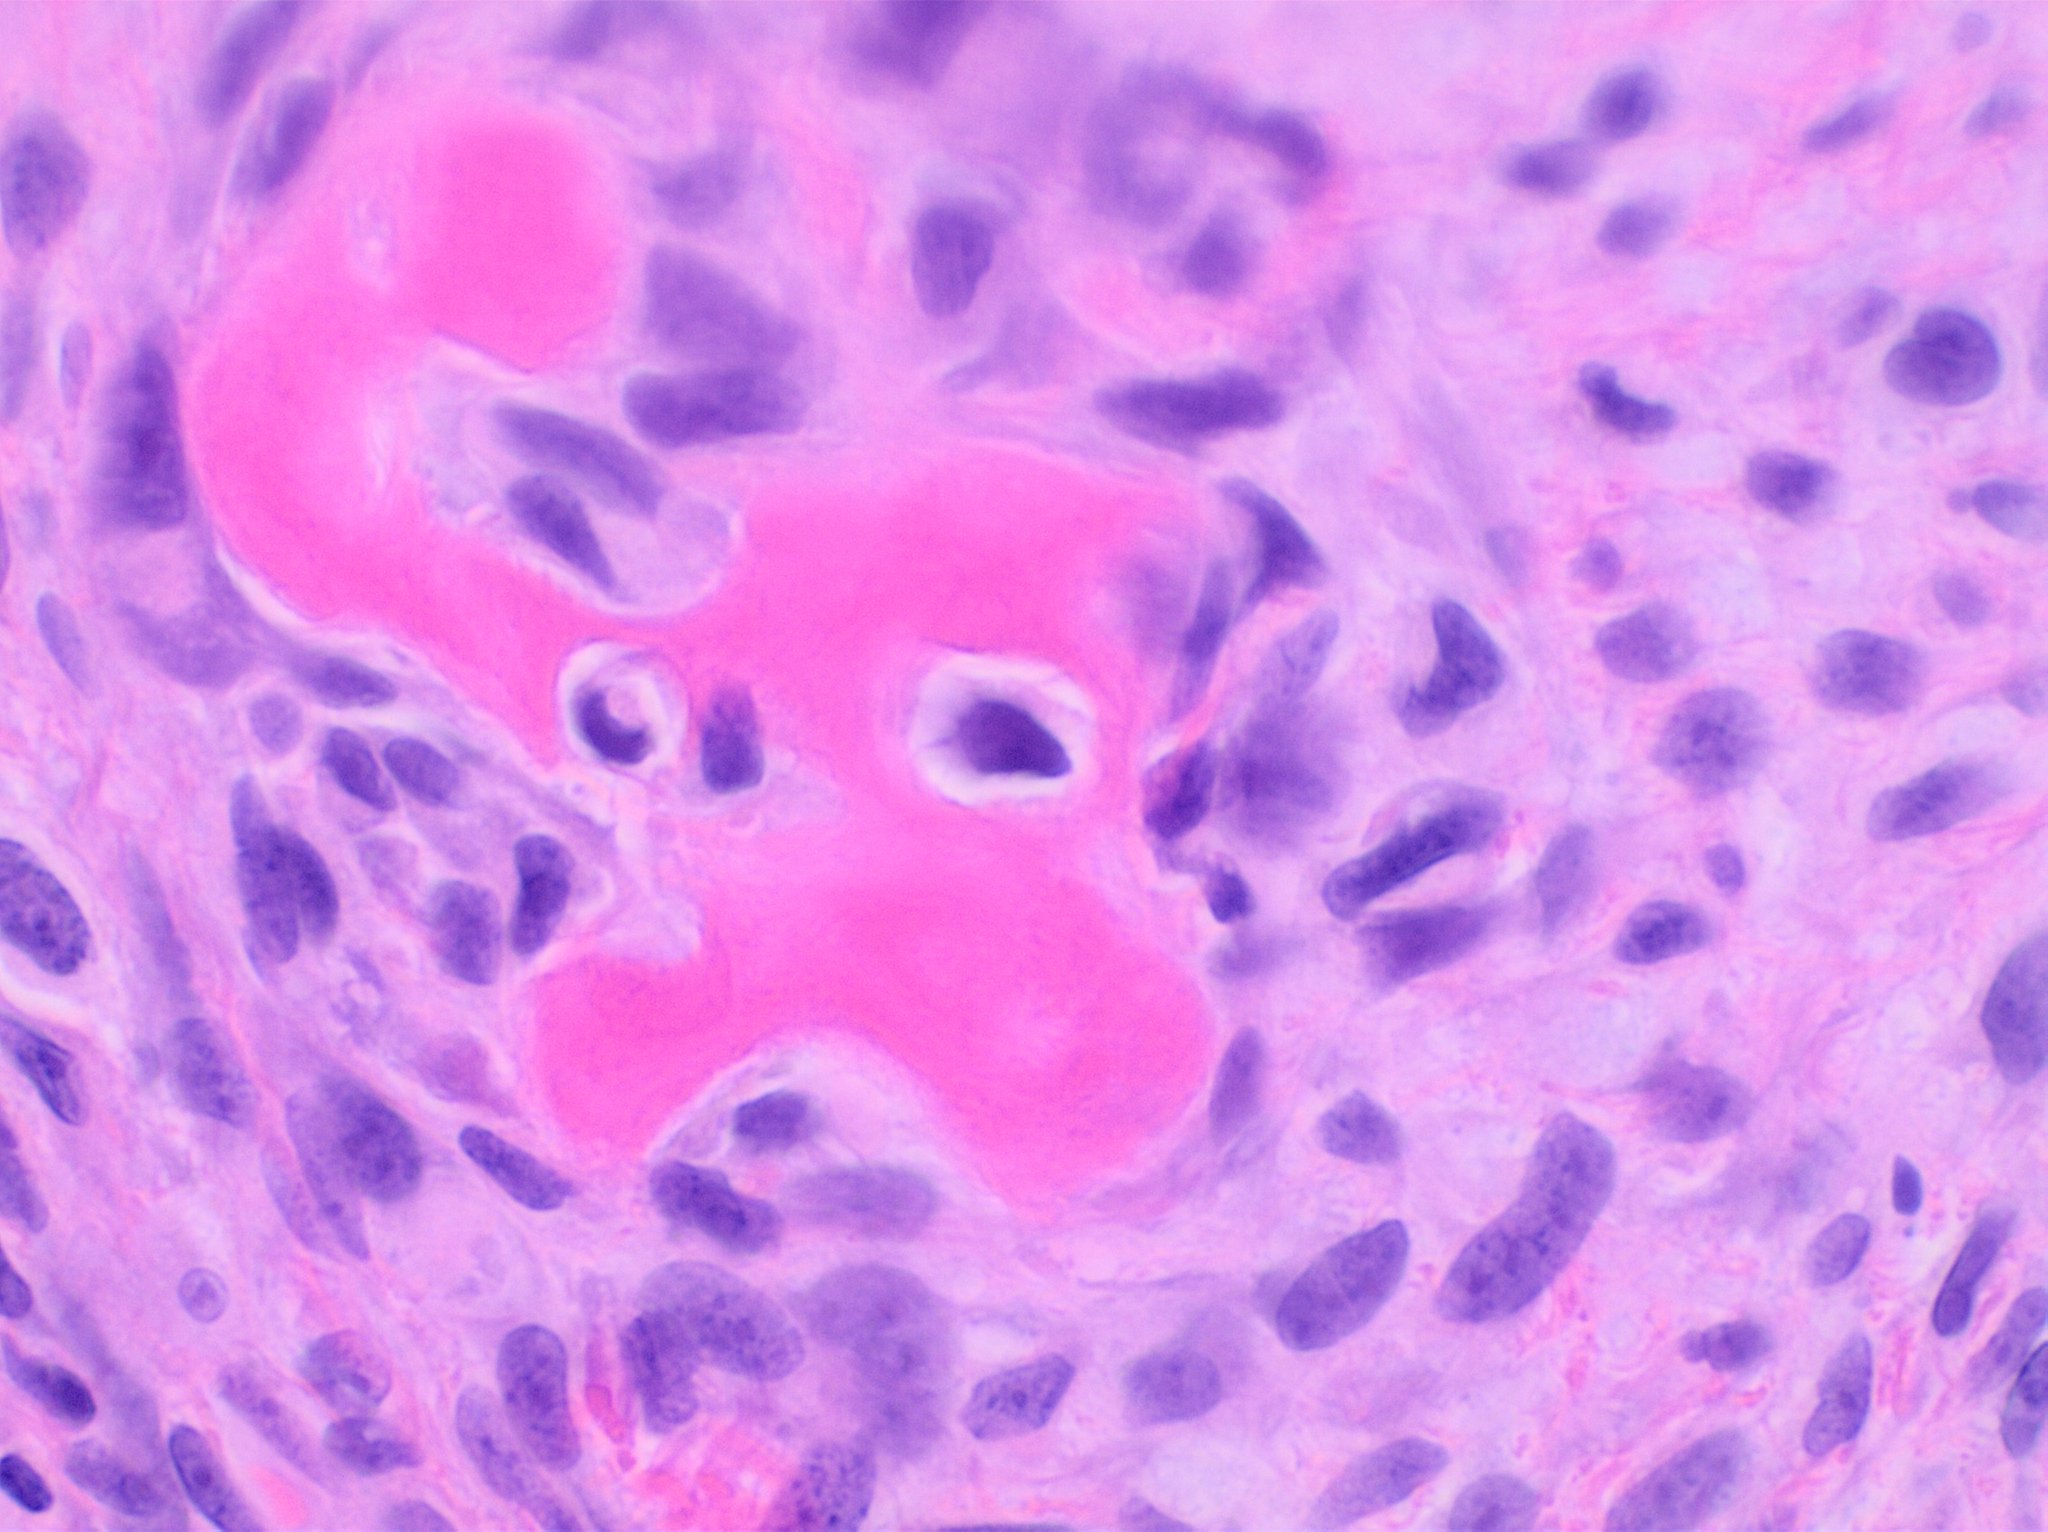
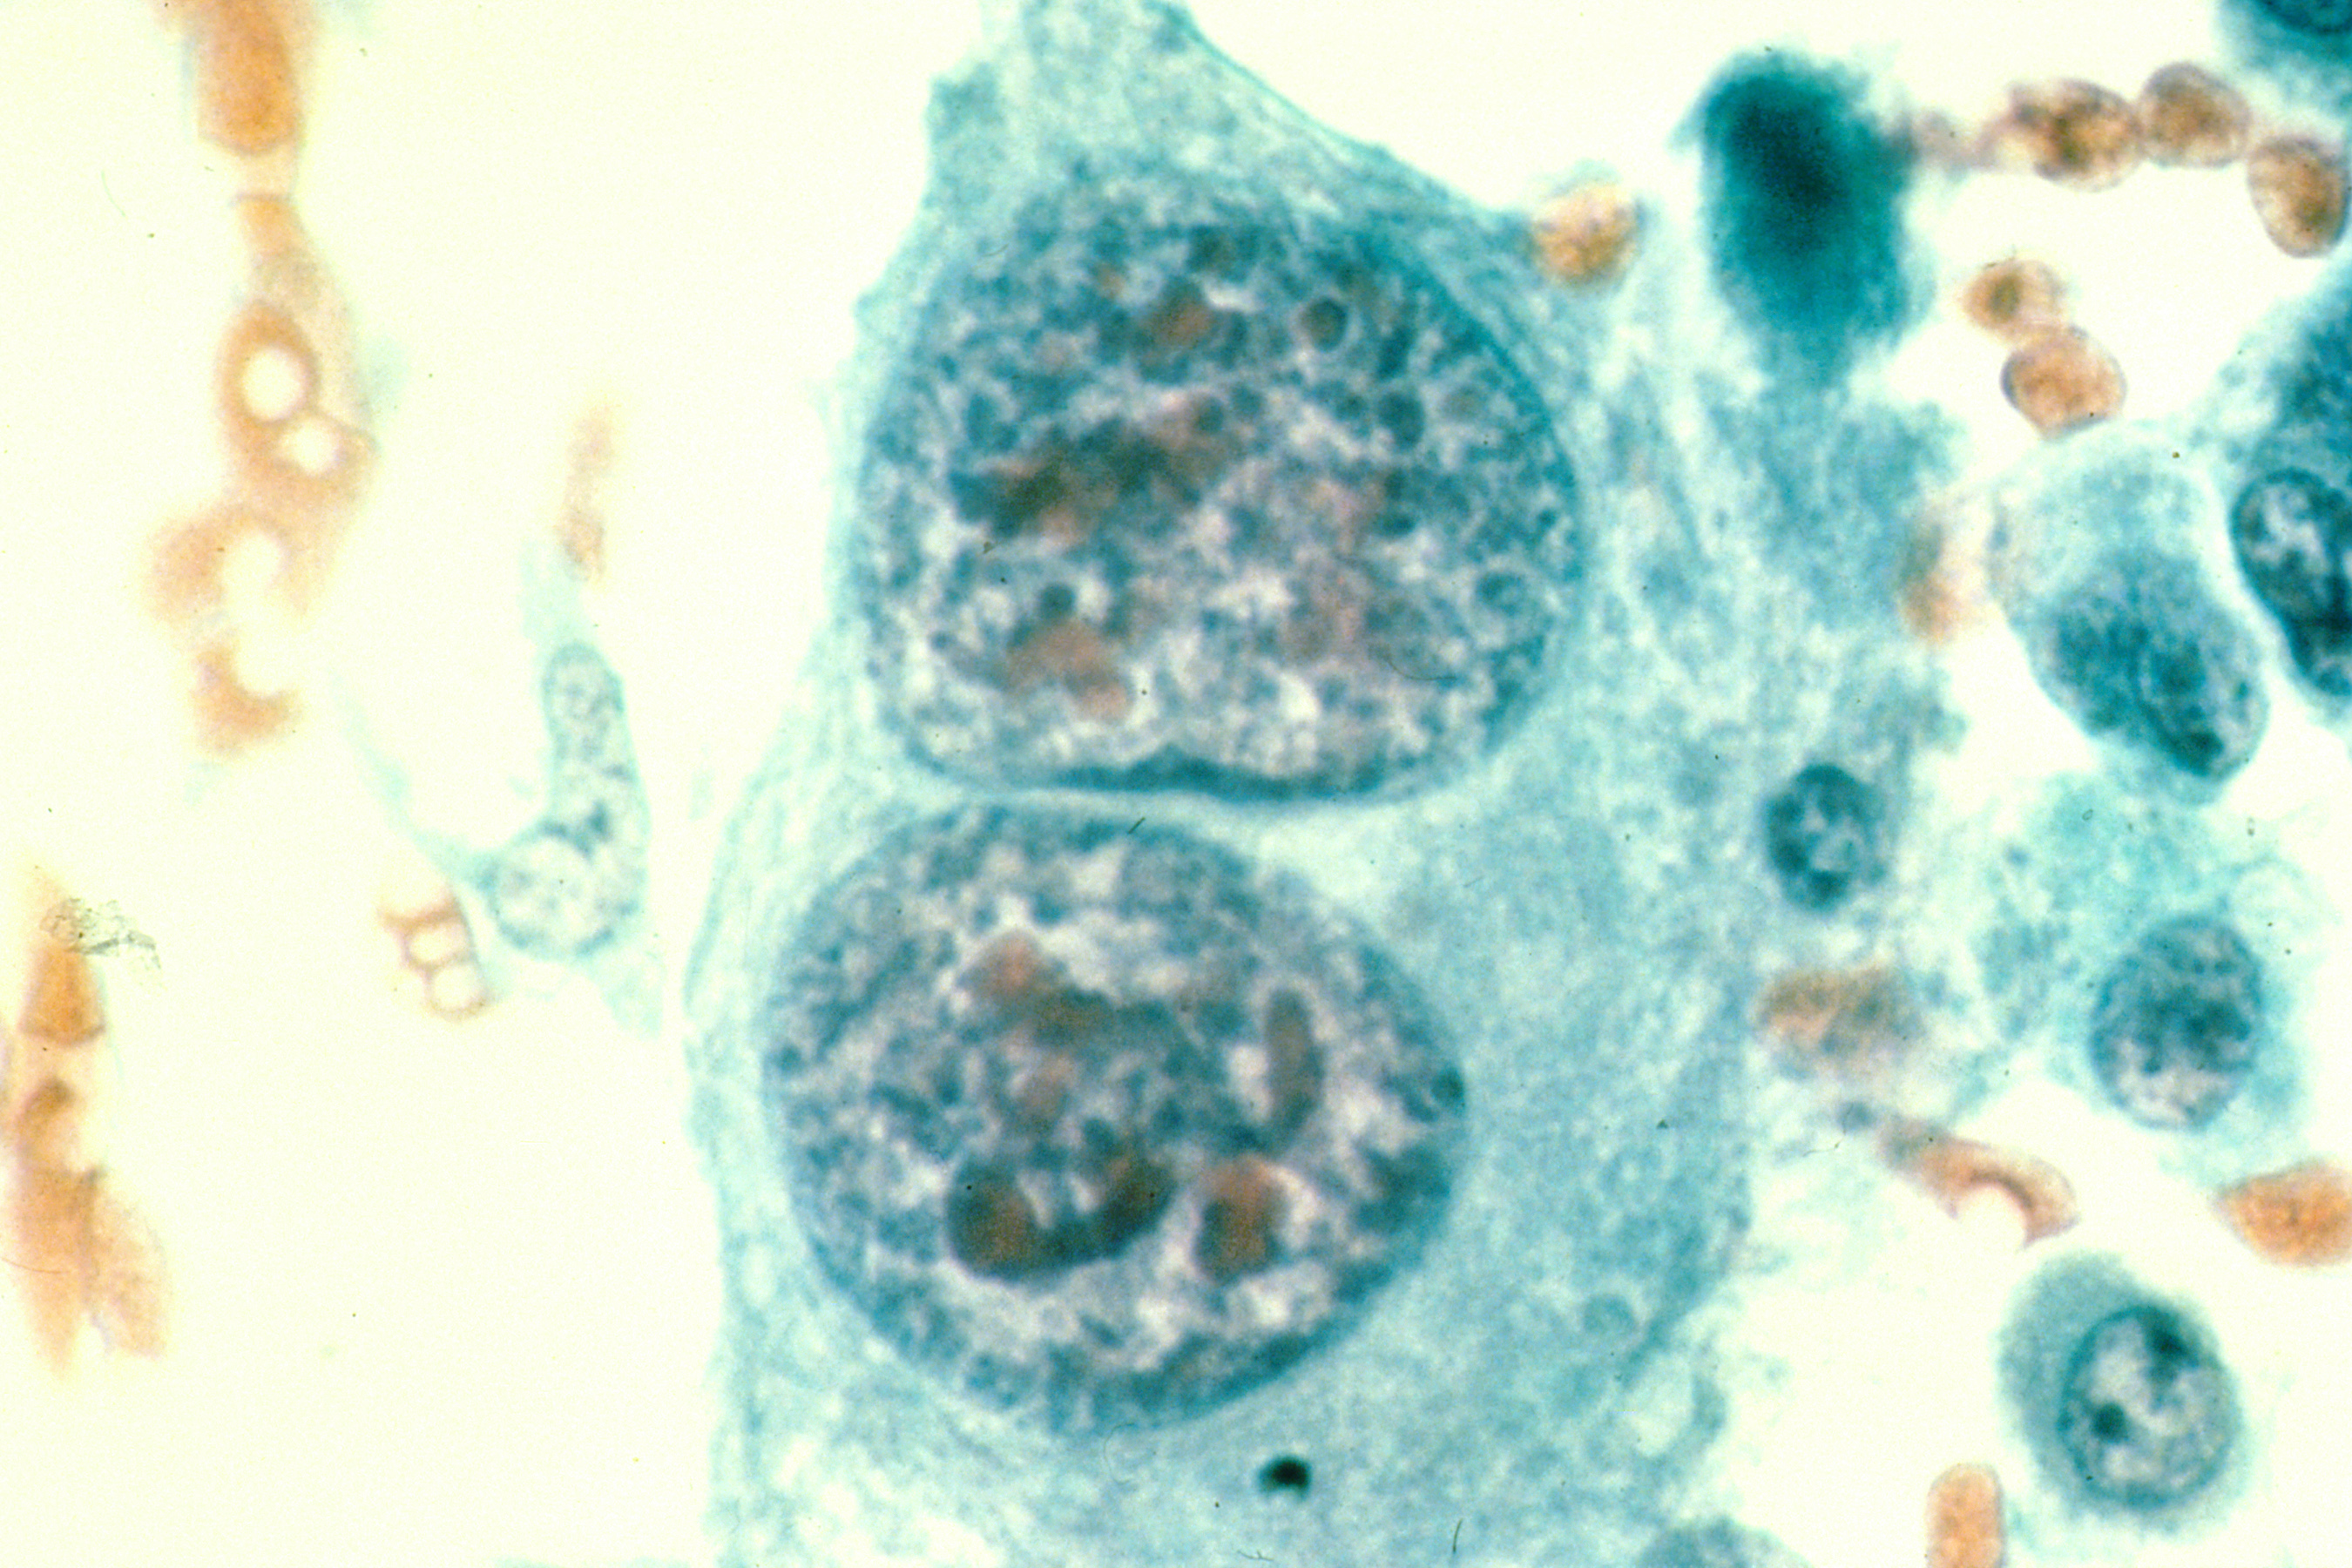
Detection usually needs a chain: suspicion, imaging or lab triage, tissue or cytology when needed, then pathology and molecular testing where it changes management.
Pros, cons and controversy
Benefits, harms and the false-positive problem.
Whole-body scans find bone lesions, but benign bone islands, fractures and arthritis can mimic disease. In known cancer, however, the threshold to image new focal pain is lower.
Sources and trials