USPSTF recommends biennial mammography for average-risk women from age 40 to 74.
Mammography, ultrasound, MRI and tissue diagnosis
Breast cancer detection starts with images, but decisions are made under the microscope.
A practical guide to warning changes, screening ages, dense breasts, mammography and tomosynthesis, ultrasound, MRI, needle biopsy, excision, histology, receptors, genetics, false positives and the cancers that screening can still miss.
US women face an approximate lifetime risk of invasive breast cancer.
dense breasts both raise risk and make mammograms less sensitive.
core biopsy and histology confirm cancer type, grade and receptors.
Brief outline
Breast cancer is not one disease.
Most breast cancers are carcinomas arising from ducts or lobules. Detection is a pathway: notice change or screen, image the area, sample tissue, classify the cancer, then stage and treat according to biology.
Demographics, risks and epidemiology
Breast cancer risk rises with age, but younger patients can develop aggressive disease, especially with inherited risk. Important risk factors include family history, prior breast cancer or high-risk lesion, dense breasts, chest radiation at a young age, BRCA1/2 and other pathogenic variants, early menarche, late menopause, nulliparity or later first pregnancy, menopausal hormone therapy, alcohol, obesity after menopause and inactivity.
Men can develop breast cancer too. A man with a firm breast lump, nipple inversion, bloody discharge or axillary node should not be reassured solely because male breast cancer is uncommon.
Do not ignore
A normal mammogram does not cancel a real symptom.
Screening tests
Mammography is the population-screening backbone.
Screening is for people without symptoms. Diagnosis is for a lump, discharge, skin change, abnormal mammogram or high-risk finding.
2D mammography and tomosynthesis
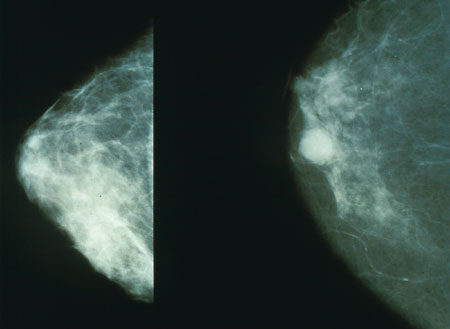
Mammography finds masses, architectural distortion and calcifications. Digital breast tomosynthesis, often called 3D mammography, can reduce tissue overlap and may reduce recall in some settings.
Ultrasound
Useful for a palpable lump, distinguishing cystic from solid lesions, guiding biopsy and evaluating axillary nodes. As extra screening in dense breasts, evidence for better hard outcomes is less settled.
Breast MRI
More sensitive than mammography, used with mammography for many high-risk patients and sometimes for extent-of-disease assessment. It can also increase false positives and biopsies.
Clinical exam and self-awareness
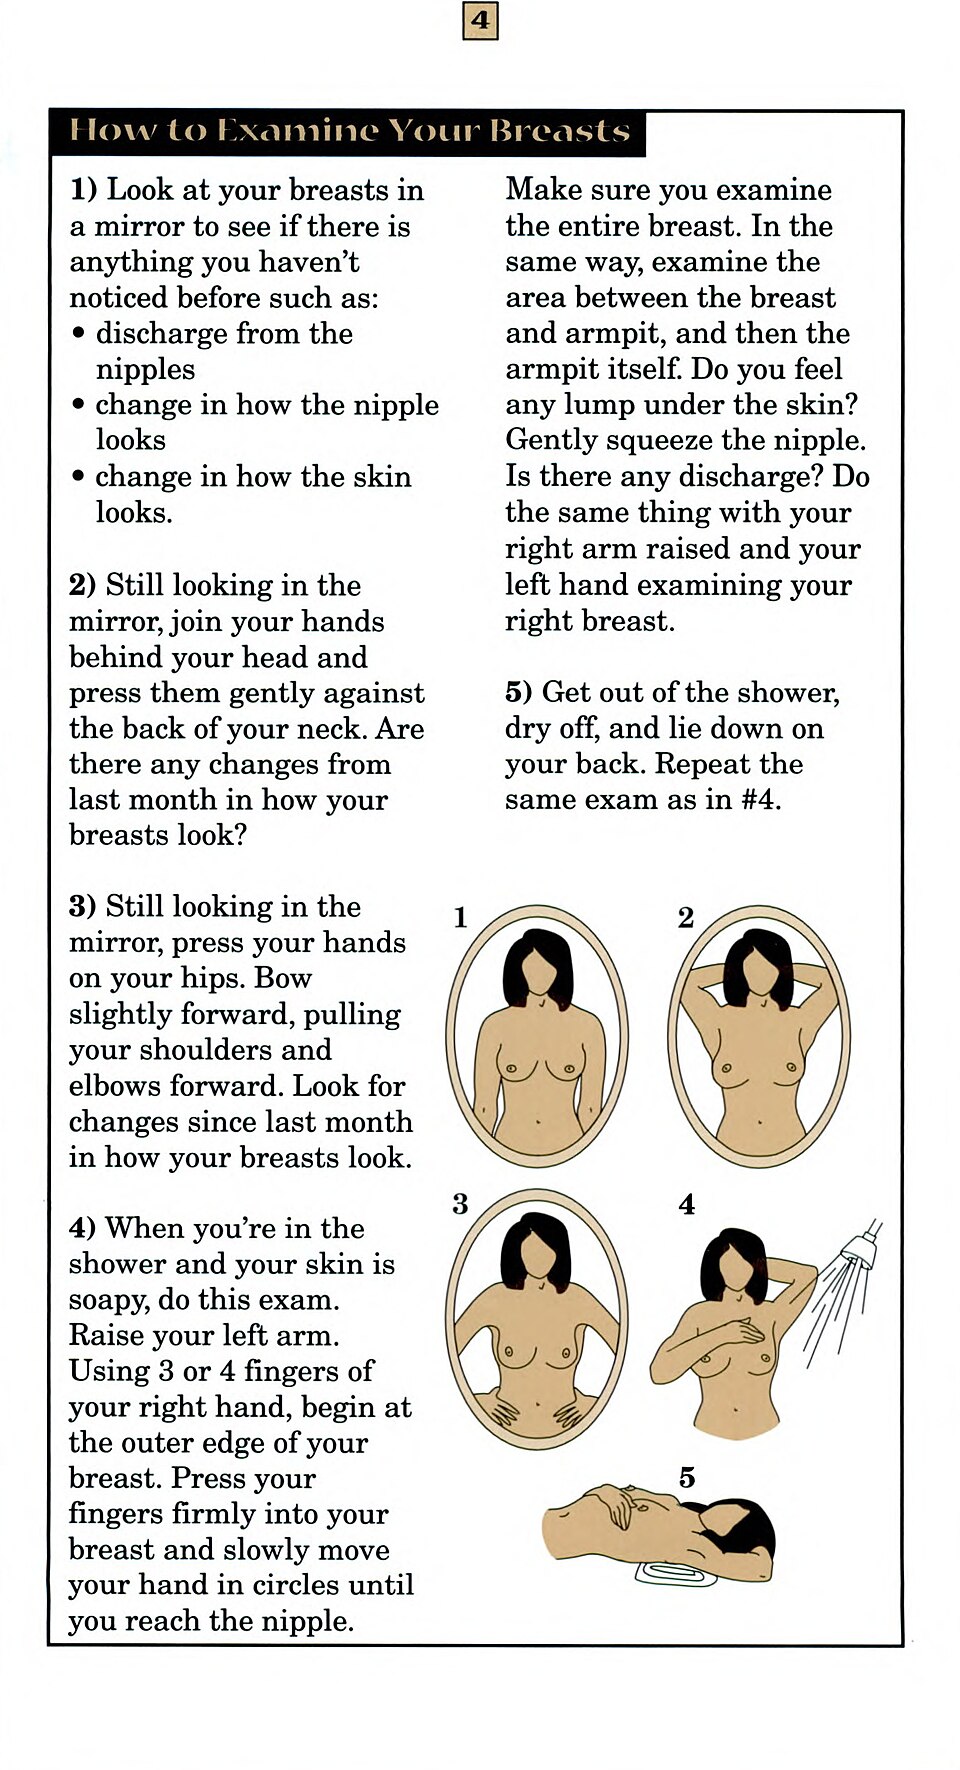
Clinical breast examination and self-awareness are not adequate screening tests alone, but they matter because symptomatic cancers can appear between scheduled mammograms.
| Program or guideline | Usual starting point | Interval | Practical note |
|---|---|---|---|
| USPSTF, US | 40 for average-risk women | Every 2 years to 74 | Evidence is insufficient for routine screening 75+ and for supplemental ultrasound/MRI solely for dense breasts after a negative mammogram. |
| American Cancer Society | Option at 40; regular screening from 45 | Annual 45-54, then biennial or continue annual | High-risk patients may need MRI plus mammography from younger ages. |
| NHS Breast Screening, England | Invitations usually age 50 to 71 | Every 3 years | Symptomatic breast clinics are separate from screening invitations. |
| BreastScreen Australia | Free screening from 40, actively invites 50-74 | Usually every 2 years | Women 40-49 and 75+ can usually attend but are not the main target invitation group. |
| Canada | Often 50-74 in organized provincial programs, with some provinces offering self-referral from 40 | Usually every 2 years | Eligibility varies by province/territory and is changing in some places toward easier access in the 40s. |
| New Zealand | Free national screening generally age 45-69 | Every 2 years | High-risk and symptomatic pathways are separate from routine BreastScreen Aotearoa invitations. |
| Ireland | BreastCheck invites women about age 50-69 | Every 2 years | Symptoms should go through GP/breast clinic rather than waiting for screening. |
| EU programs | Many organized programs invite roughly age 50-69 or 50-74 | Usually every 2 years, sometimes 2-3 years | Countries differ on upper age, starting age, density policies and tomosynthesis use. |
Dense breasts
Dense tissue is both a risk factor and a masking problem.
On mammography, dense breast tissue appears white, and many cancers also appear white. This can lower mammographic sensitivity. Since 2024 in the US, MQSA breast-density notification rules require clearer patient notification about density.
Diagnosis
Suspicious imaging leads to needle biopsy, not guessing.
Breast imaging reports usually use BI-RADS categories. BI-RADS 0 means more imaging is needed; 1-2 are negative/benign; 3 is probably benign with short follow-up; 4-5 usually require biopsy; 6 means known cancer.
Hookwire localization is common, but it is not the biopsy itself
If a suspicious area cannot be felt, radiology may localize it before surgery using a hookwire, radioactive seed, magnetic seed or radar reflector. That guides the surgeon to the mammographic or ultrasound target for excision. It is a targeting step for surgery, separate from the earlier needle biopsy that made or suggested the diagnosis.
Sentinel lymph node biopsy is staging, not screening
For many invasive breast cancers, surgeons sample the first draining lymph node or nodes, usually in the axilla/armpit. If the sentinel nodes are negative, many patients can avoid full axillary node clearance, which lowers the risk of arm lymphoedema, or lymphedema in US spelling, numbness and shoulder problems. A suspicious axillary node on ultrasound may be needle-biopsied before surgery.
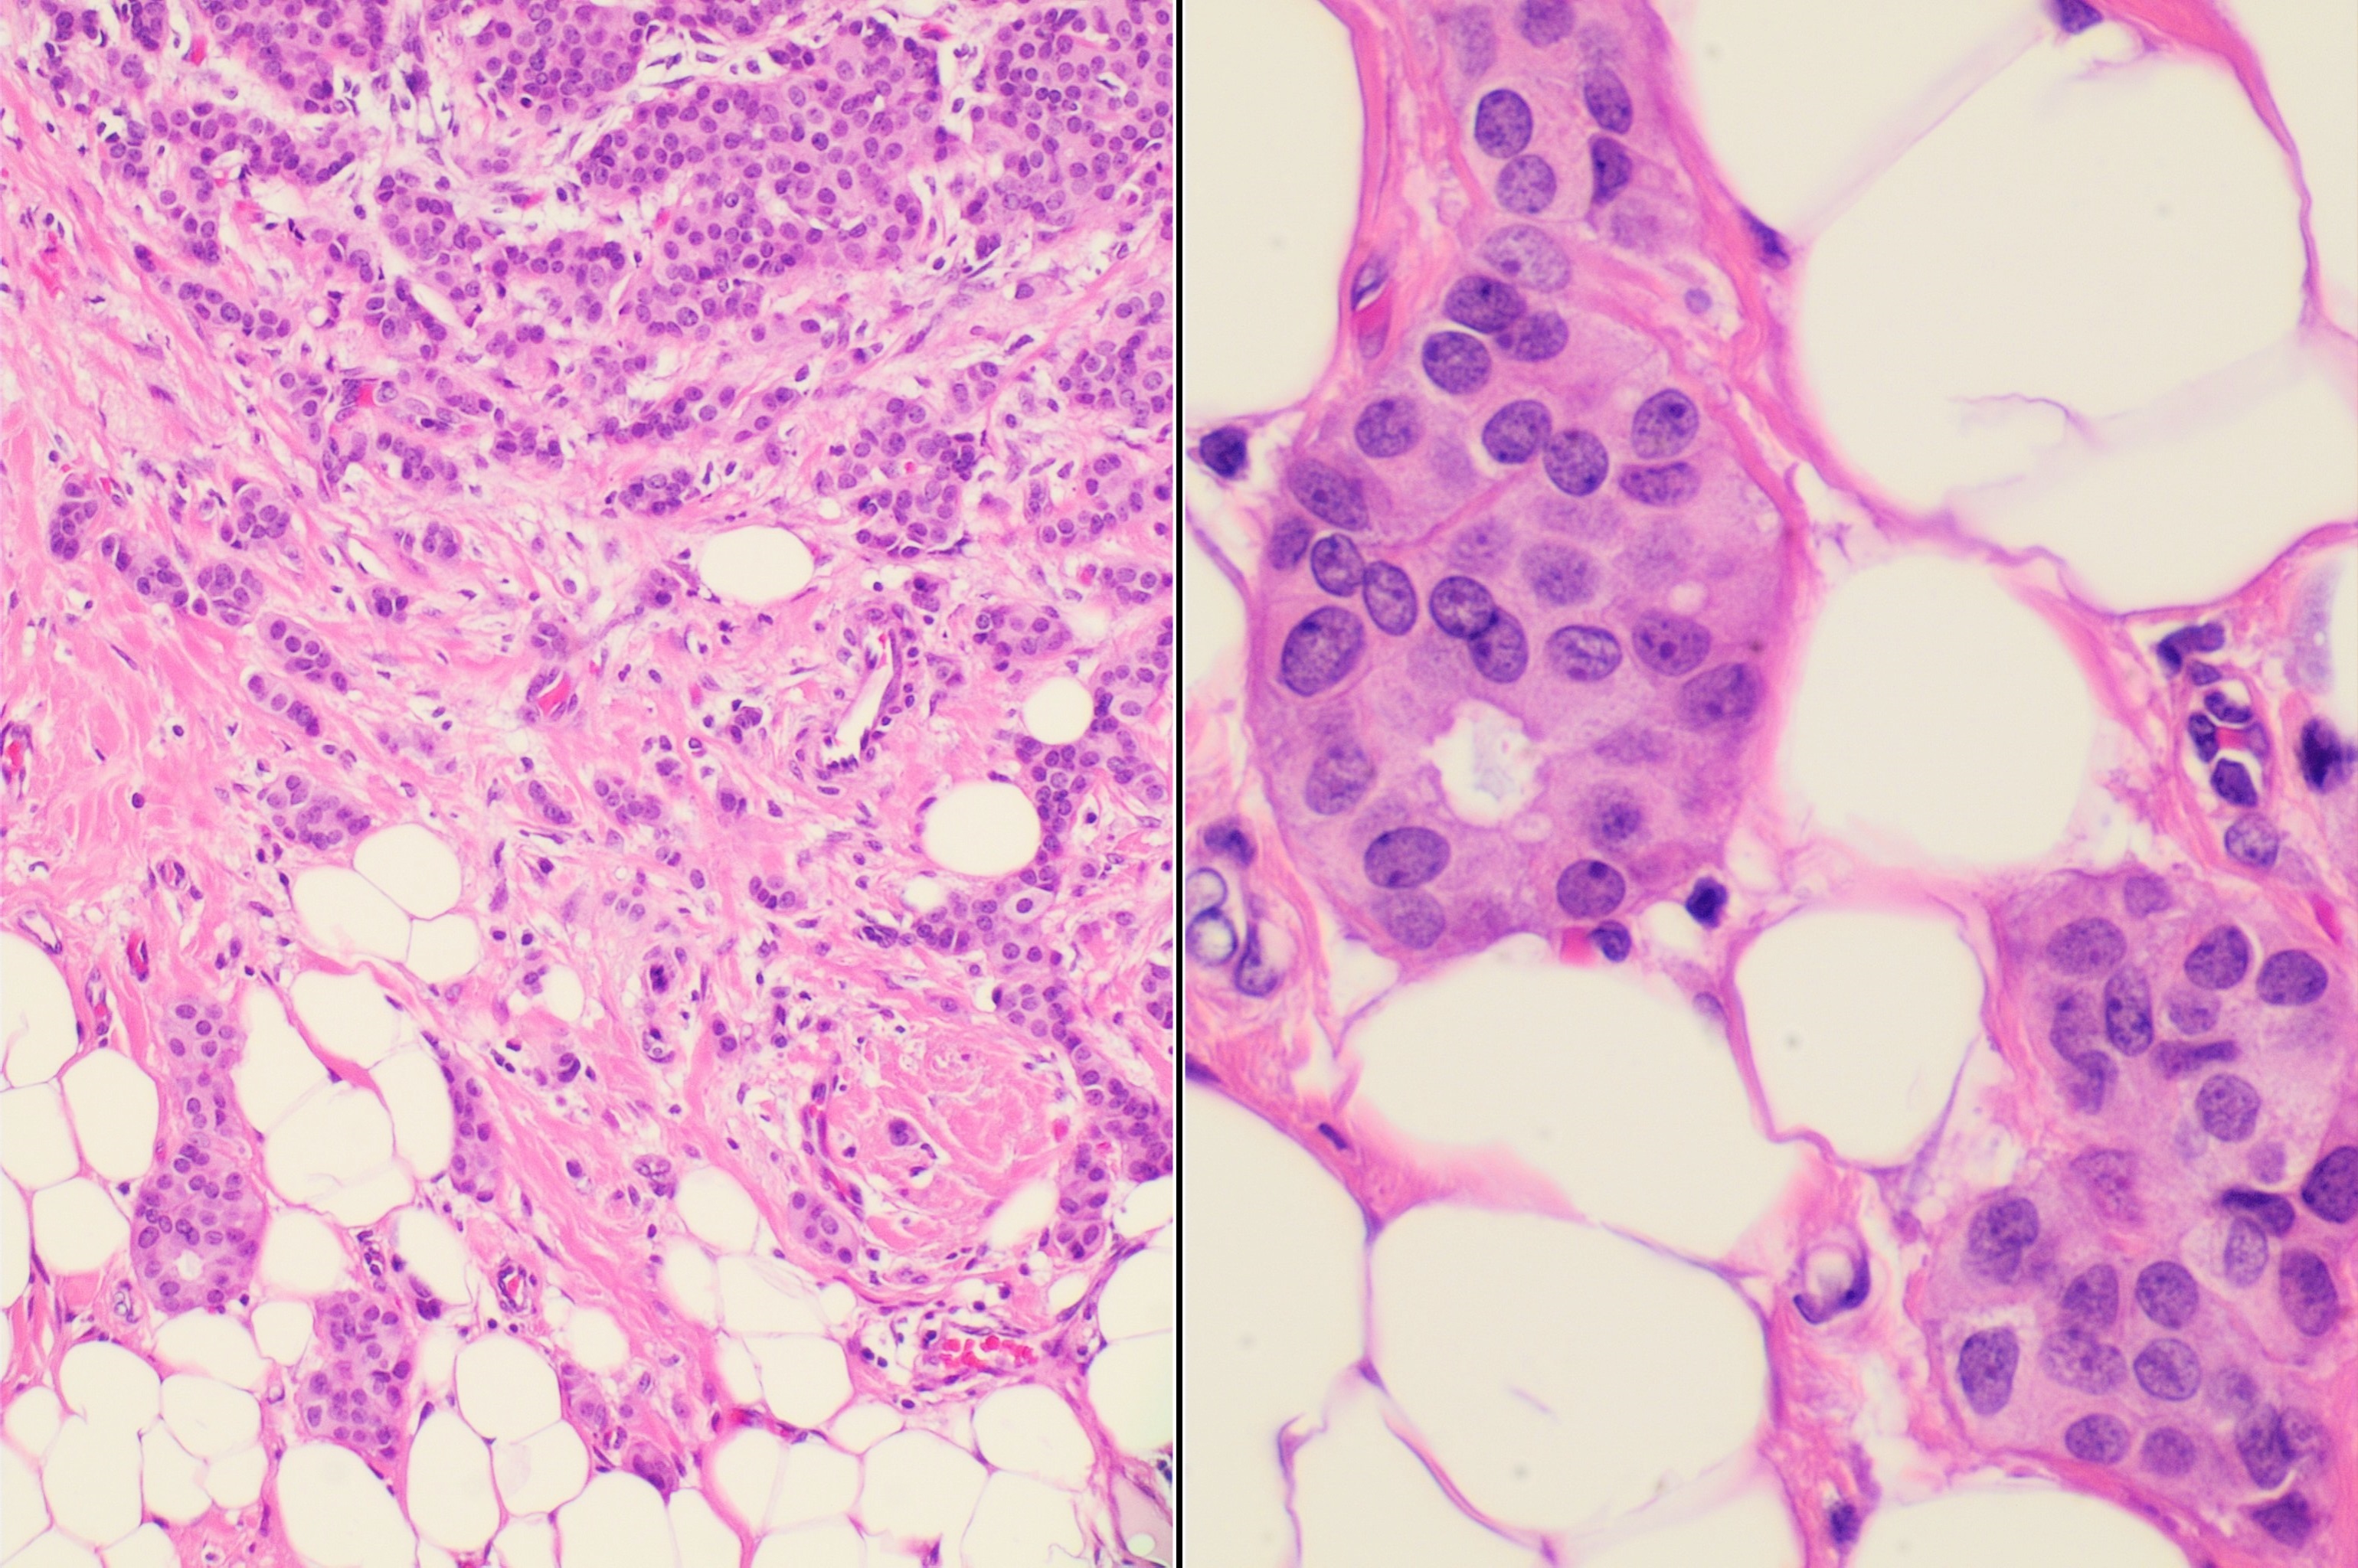
What pathology may show
Type and receptors change both prognosis and detection strategy.
Family history and genetics
Genetic risk changes the age and intensity of detection.
Pros, cons and outcomes
Mammography has mortality evidence, but it also creates recalls, biopsies and overdiagnosis.
The aim is not to find every microscopic abnormality. It is to reduce deaths and advanced cancers while keeping false positives, false negatives, anxiety and overtreatment proportionate.
Earlier stage and fewer deaths
Screening mammography can find cancers before symptoms and has evidence for reducing breast-cancer mortality. It works best when abnormal results get timely diagnostic imaging, biopsy and treatment.
False positives and overdiagnosis
Recalls and benign biopsies are common enough to matter, especially with annual testing and younger age. DCIS and indolent tumors create the hard question: did detection prevent death or create treatment for a lesion that may not have harmed the patient?
New blood and AI tests
AI mammography can assist readers and may improve detection or reduce workload, but must be judged by interval cancers, advanced cancers, false positives and outcomes. Blood-only multi-cancer tests should not replace mammography.
Risk-adapted detection
Average-risk population screening can be mammography-led. High-risk patients may need MRI and genetics. Symptomatic patients need diagnosis, not a routine screening slot.
Sources and reviews
Useful places to start.
USPSTF breast screening 2024Biennial mammography from 40 to 74; dense-breast supplemental screening evidence gaps.
NCI breast screening overviewMammography, MRI, ultrasound, exam, false positives, overdiagnosis and false negatives.
American Cancer Society statisticsCurrent US breast cancer incidence, deaths, lifetime risk and male breast cancer figures.
FDA MQSA density ruleUS mammography reporting and breast-density notification changes.
NCI benign and precancerous breast conditionsFibroadenoma, cysts, papilloma, ADH, ALH, LCIS and phyllodes context.
NCI breast cancer treatment overviewDetection links to stage, receptors, DCIS, inflammatory cancer, triple-negative disease and Paget disease.
Open screening review: ESR Essentials / EUSOBIOpen-access review of mammography, tomosynthesis, ultrasound, MRI, contrast-enhanced mammography, false positives and overdiagnosis.
Open imaging reviewReview of conventional and emerging breast imaging modalities, BI-RADS, biopsy triggers and future diagnostic directions.
Open diagnostics reviewFrom population screening through molecular subtypes, AI, liquid biopsy and precision diagnostic workup.
NHS breast screeningEngland screening invitations, age range and every-3-years program structure.
BreastScreen AustraliaFree breast screening and target invitation ages in Australia.
Canada breast screening overviewNational public-health overview; provincial and territorial program details vary.