insulinoma can cause dangerous hypoglycemia.
Symptoms, risk, screening and diagnostic confirmation
Detect Neuroendocrine Tumors is about choosing the right test for the right risk.
A NET detection guide covering functioning and non-functioning NETs, carcinoid syndrome, insulinoma hypoglycemia, chromogranin A limits, 5-HIAA, CT/MRI, EUS/endoscopy, gallium DOTATATE PET/CT and Ki-67 grade.
non-functioning NETs may grow large before detection.
helps mainly serotonin-secreting carcinoid tumors.
gallium PET/CT can localize SSTR-positive NETs.
Brief outline
What neuroendocrine tumors means.
Neuroendocrine tumors can arise in bowel, pancreas, lung and other sites. Functioning NETs secrete hormones and may announce themselves; non-functioning NETs may grow silently until they are large, metastatic or found incidentally.

Detection frame
Screening is for people without symptoms. Diagnosis is for symptoms, abnormal examination, family history, imaging findings or abnormal labs. The same test can be sensible in one setting and misleading in another.
Do not ignore
Symptoms and signs not to ignore.
Risk and genetics
Demographics, risks and genetics.
Screening
Who should actually be screened?
There is no average-risk population screening. Genetic syndromes and known precursor conditions require specialist surveillance.
5-HIAA urine/plasma
Useful for serotonin-secreting carcinoid tumors; diet/drugs can interfere.
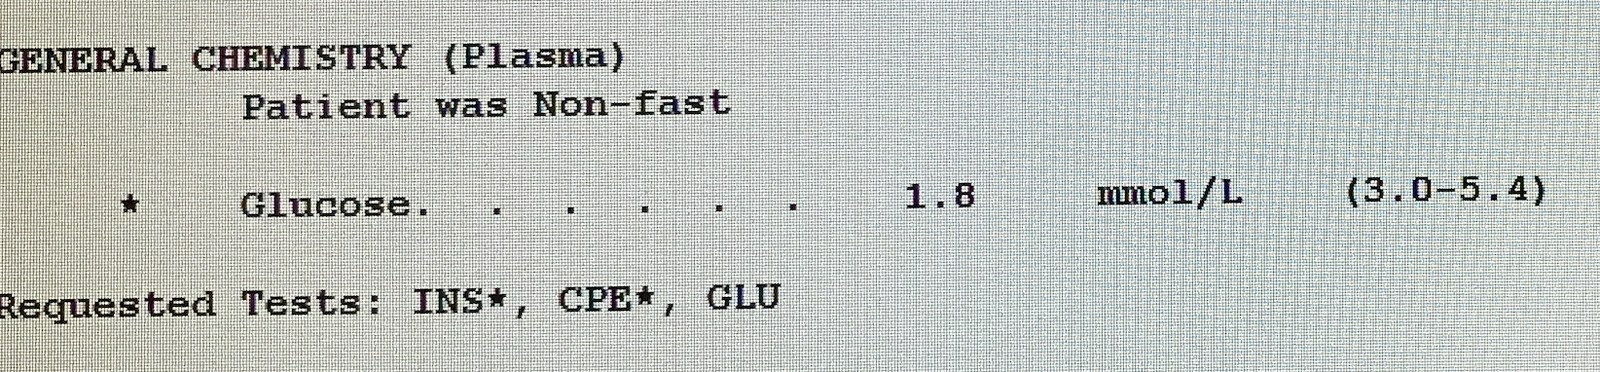
Glucose, insulin, C-peptide during hypoglycemia
Confirms inappropriate insulin secretion before localization.
Chromogranin A
Can be elevated by PPIs, kidney disease and other causes; poor as blind screening.
CT/MRI multiphase
Finds primary tumors and liver metastases.
Ga-68 DOTATATE PET/CT
A gallium DOTATATE scan shows somatostatin-receptor-positive disease; some insulinomas need additional or different localization.
Biopsy with Ki-67 grade
Grade and differentiation drive prognosis and treatment.
Images, labs and tissue
Useful tests and what they can miss.
Detection usually needs a chain: recognizing the syndrome, proving the biochemistry at the time of symptoms, localizing the lesion, then confirming grade and biology when tissue is needed. Insulinoma is a good example: the glucose, insulin and C-peptide pattern matters before the scan is interpreted. A meter reading of 1.7 mmol/L converts to about 31 mg/dL (31 mg/100 mL), which is dangerously low.

Pros, cons and controversy
Benefits, harms and the false-positive problem.
NET blood markers can mislead badly if used as screening in low-risk people. The benefit is highest when symptoms, imaging or inherited risk point to the diagnosis. Functioning tumors such as insulinoma may be detected because the hormone syndrome is dramatic; non-functioning NETs are riskier for delay because they can simply grow.
Sources and trials