with biopsy is the key diagnostic test.
Gastroscopy, biopsy and H. pylori risk
Stomach cancer detection depends on upper endoscopy when symptoms or risk justify it.
There is no broad average-risk screening program in many low-incidence countries, but high-incidence countries use upper endoscopic or radiographic programs. Alarm symptoms need diagnosis.
is a major modifiable risk factor.
have organized screening because incidence is higher.
CDH1 hereditary diffuse gastric cancer changes prevention and surveillance.
Brief outline
Most stomach cancers are gastric adenocarcinomas.
Cancer can arise from chronic inflammation, atrophic gastritis, intestinal metaplasia, dysplasia or hereditary pathways. Diffuse-type cancers can infiltrate subtly and may be harder to see.
Detection frame
The detection question is whether symptoms are alarm features, whether H. pylori or premalignant stomach changes are present, and whether the patient comes from a high-incidence or inherited-risk group.
Do not ignore
Alarm symptoms should not be treated as simple indigestion.
Risk and genetics
H. pylori and inherited risk matter.
Screening
Screening depends strongly on country and risk.
Japan and South Korea screen because gastric cancer is common enough for population programs. In many lower-incidence countries, gastroscopy is symptom-driven or risk-driven rather than routine for everyone.
Gastroscopy / upper GI endoscopy
Best route to see the stomach directly when alarm symptoms or suspicious imaging are present.
Biopsy and histology
Confirms adenocarcinoma, lymphoma, GIST or benign disease.
H. pylori testing
Breath, stool antigen, serology or biopsy-based tests; treatment matters.
CT chest/abdomen/pelvis
Assesses spread and operability.
Endoscopic ultrasound (EUS)
Can help local T/N staging in selected early or junctional tumors.
Staging laparoscopy
May find peritoneal spread missed on CT.
Images, labs and tissue
Gastroscopy plus biopsy is central.
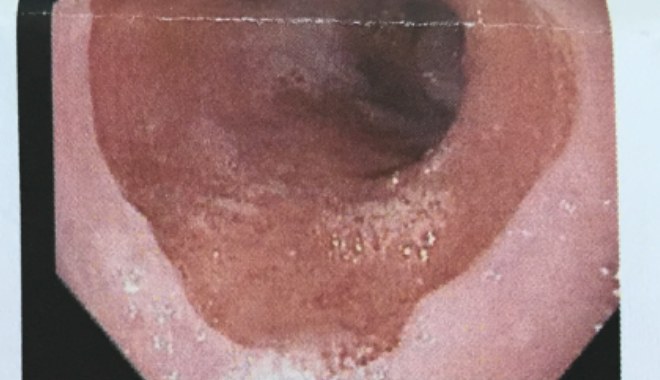
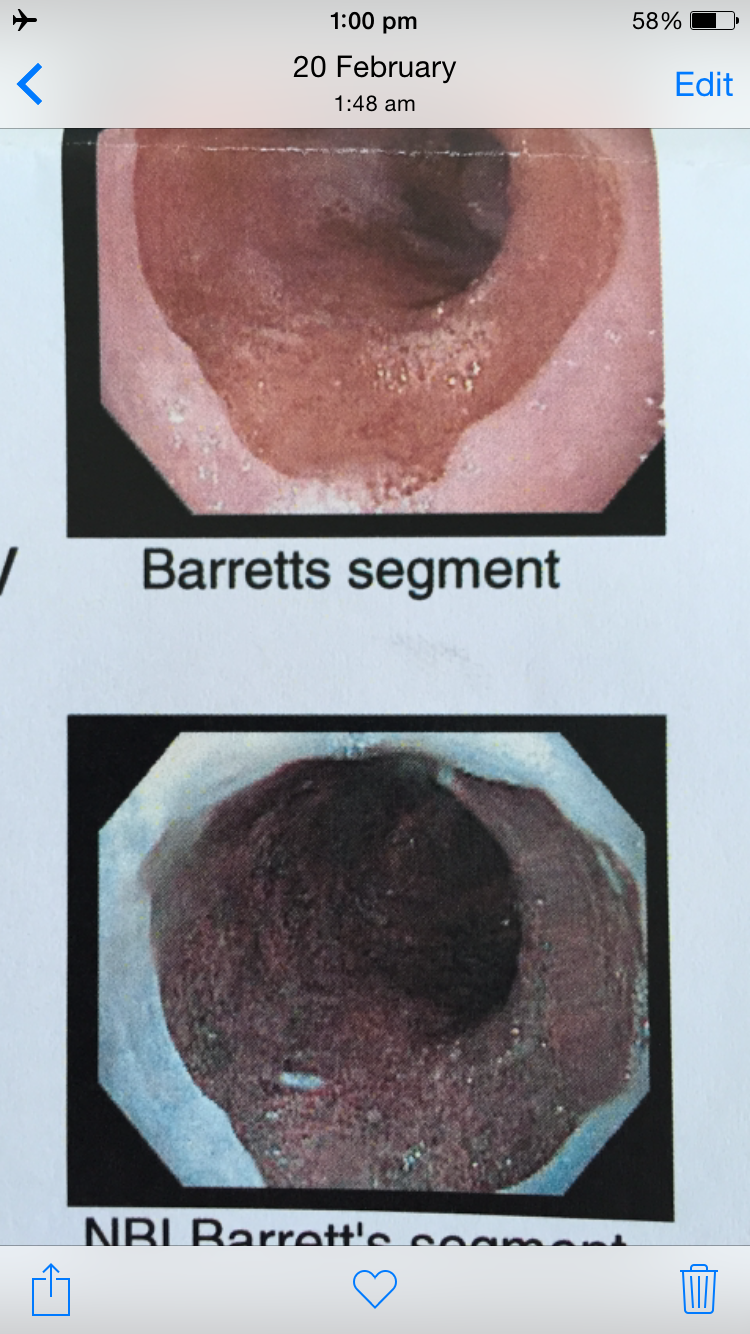
Gastroscopy, also called upper GI endoscopy, allows direct inspection of the stomach, targeted biopsies and mapping of suspicious mucosa. The same examination may extend through the pylorus into the duodenum as gastroduodenoscopy/duodenoscopy. CT, EUS and laparoscopy may stage confirmed cancer.
Pros, cons and controversy
The controversy is geography and overuse.
In high-incidence countries, screening can find early gastric cancer that is curable endoscopically or surgically. In low-incidence countries, routine gastroscopy for everyone would create cost, sedation risk and many benign findings.
Sources and trials